
What Are the Top Spine Surgery Techniques?
Choosing among the top spine surgery techniques requires more than comparing modern equipment. It requires understanding the patient’s pain, neurological findings, spinal stability, and daily goals. A slipped disc, narrowed canal, fracture, or deformity may demand very different solutions. Sometimes, physical therapy and careful observation remain safer choices. Surgery is not automatically the best answer.
Spine surgeon Dr. Alexander Vaccaro has emphasized, “There is no one-size-fits-all approach to spine surgery.” That principle guides responsible decision-making. Common techniques include decompression, spinal fusion, artificial disc replacement, minimally invasive surgery, and endoscopic procedures. Decompression removes pressure around a nerve. Fusion stabilizes painful or unstable segments. Artificial discs aim to preserve motion in selected patients. Small incisions may reduce muscle injury, but they do not remove surgical risk.
The details matter.
A surgeon may use navigation, intraoperative imaging, or robotic assistance for greater accuracy. Yet technology cannot replace clinical judgment. Recovery may involve walking carefully, wound monitoring, rehabilitation, and patience. Results also depend on smoking status, bone quality, weight, diabetes control, and realistic expectations. Some procedures relieve leg pain better than back pain. Others may require later treatment. Evidence continues to change, and no technique deserves praise without context. This guide examines how leading spine surgery methods work, where they help, and what their limitations may mean for real patients. A qualified spine specialist should review imaging and symptoms before any decision.
What Spine Surgery Is Designed to Treat
What Are the Top Spine Surgery Techniques? What Spine Surgery Is Designed to Treat
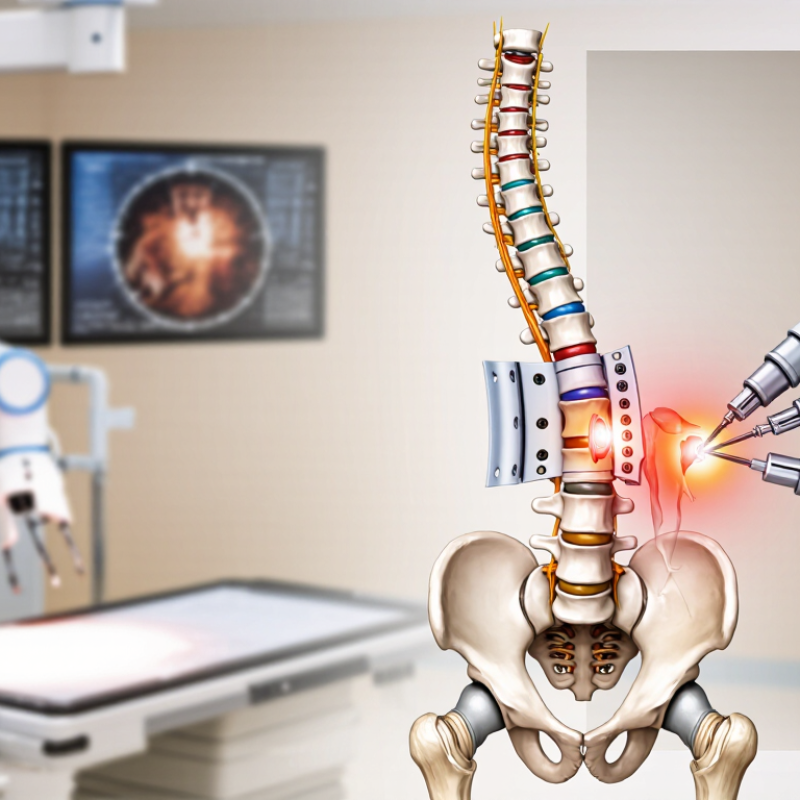
Spine surgery is designed to relieve pressure, restore stability, or correct serious structural problems. It is not simply an answer to back pain. The World Health Organization reported that low back pain affected about 619 million people worldwide in 2020. However, only a small proportion require surgery. Persistent nerve compression, spinal instability, deformity, fractures, tumors, or infection may justify a surgical discussion.
Decompression procedures remove bone or disc material pressing on nerves. They can address spinal stenosis, leg weakness, numbness, or sciatica. Discectomy targets a herniated disc, often through a small incision. Fusion joins unstable vertebrae using bone graft and internal support. Disc replacement aims to preserve movement in selected patients. Technique matters, but diagnosis matters more. A narrow canal on a scan does not always explain the pain.
Evidence remains imperfect. The North American Spine Society guideline supports surgery for selected lumbar disc herniation patients when symptoms persist despite suitable nonoperative care. The guideline also emphasizes matching symptoms with imaging and examination findings. That step can prevent unnecessary treatment. Recovery may involve a quiet room, short walks, wound checks, and months of rehabilitation. Risks include infection, nerve injury, blood clots, nonunion, or continuing pain. A surgeon should explain these possibilities plainly. Surgery can help greatly, but it is not a guaranteed reset.
What Are the Top Spine Surgery Techniques? - What Spine Surgery Is Designed to Treat
| Surgical Technique | Primary Purpose | Conditions It May Treat | How It Works | Important Considerations |
|---|---|---|---|---|
| Discectomy | Relieve pressure on a spinal nerve | Herniated disc with persistent sciatica, arm pain, numbness, or weakness | Removes the portion of disc material pressing on a nerve root or, less commonly, the spinal cord | Often considered after nonsurgical treatment fails or when significant neurological symptoms are present |
| Laminectomy | Create more space for the spinal cord or nerve roots | Spinal stenosis, degenerative narrowing, and some cases of spinal cord compression | Removes part or all of the lamina, the bony arch at the back of a vertebra | Fusion may be added if removing bone could cause or worsen spinal instability |
| Foraminotomy | Open the passageway where a nerve exits the spine | Foraminal stenosis, bone spurs, and nerve-root compression | Removes bone or soft tissue narrowing the neural foramen | The surgical plan depends on the location and cause of compression, as well as spinal stability |
| Spinal Fusion | Stabilize painful or structurally unstable spinal segments | Spinal instability, selected cases of spondylolisthesis, deformity, fracture, tumor, or recurrent disc problems | Joins two or more vertebrae so they heal into a single stable segment, usually with bone graft and fixation | May reduce motion at the fused level; healing time and risks vary with the patient and procedure |
| Cervical Decompression and Fusion | Relieve pressure in the neck and stabilize the cervical spine | Cervical radiculopathy, myelopathy, degenerative disc disease, and selected instability | Removes the compressive disc, bone, or ligament and fuses the affected level when stability or alignment requires it | Spinal cord symptoms require careful assessment because untreated compression may cause lasting impairment |
| Artificial Disc Replacement | Remove a damaged disc while preserving motion at the treated level | Selected cervical or lumbar disc degeneration with nerve-related symptoms | Replaces the diseased disc with a motion-preserving implant after decompression | Not appropriate for every patient; advanced facet arthritis, instability, deformity, or severe bone weakness may limit eligibility |
| Vertebral Augmentation | Stabilize a painful compressed vertebral body | Selected painful vertebral compression fractures, often related to osteoporosis | Places bone cement into the fractured vertebra through a needle or small access channel | Fracture age, pain source, imaging findings, and medical risk must be evaluated before treatment |
| Minimally Invasive Spine Surgery | Perform decompression or stabilization through smaller access points when appropriate | Selected disc herniation, stenosis, instability, and degenerative conditions | Uses specialized instruments, tubular access, or image guidance to limit disruption of surrounding tissues | It is an approach rather than a single operation; suitability depends on anatomy, diagnosis, and surgeon experience |
| Spinal Deformity Correction | Improve alignment, balance, stability, and sometimes neurological function | Progressive scoliosis, kyphosis, flat-back deformity, or complex degenerative imbalance | Uses correction techniques, decompression when needed, and fusion across selected spinal levels | These procedures can be extensive and require detailed imaging, medical optimization, and individualized risk assessment |

How Surgeons Evaluate and Select a Spine Procedure
What Are the Top Spine Surgery Techniques?
How Surgeons Evaluate and Select a Spine Procedure
Choosing a spine procedure begins with the patient, not the operating room. Surgeons review pain patterns, muscle weakness, reflexes, walking ability, and daily limitations. They also examine MRI or CT images beside the physical findings. An abnormal scan alone rarely justifies surgery.
Decompression may relieve pressure around a nerve or the spinal cord. Fusion can stabilize painful movement between vertebrae. Artificial disc replacement may preserve motion in carefully selected patients. Minimally invasive approaches can reduce tissue disruption, but they are not suitable for every spinal problem. The best technique depends on anatomy, instability, bone quality, previous operations, and overall health.
Surgeons also discuss nonoperative care, including physical therapy, medication, and targeted injections. Urgent weakness or loss of bladder control changes the conversation. So does smoking, diabetes, or poor bone density. Reliable decisions consider complication risks, recovery time, and the patient’s work and home responsibilities. A second opinion can clarify difficult choices.
Imaging can mislead.
No checklist is perfect. A surgeon may recommend a different procedure after reviewing new symptoms or updated images. Evidence from clinical guidelines and peer-reviewed studies supports the discussion, but individual judgment still matters. Patients should ask what problem surgery will treat, what happens without it, and how success will be measured.
What Are the Top Spine Surgery Techniques?
Typical operative-time ranges help surgeons compare procedure complexity alongside anatomy, diagnosis, instability, and patient health.
The chart shows approximate operative-time midpoints commonly reported for uncomplicated cases. Actual duration varies with the number of spinal levels, revision surgery, deformity, navigation, medical risk, and surgeon experience. Operative time is only one factor in procedure selection.
Common Open Spine Surgery Techniques
Open spine surgery techniques remain important when nerve compression, spinal instability, or deformity cannot be treated safely with smaller procedures. These operations use an incision to expose the affected vertebrae directly.
A laminectomy removes part of the lamina, creating more room for the spinal cord or nerves. A laminotomy removes only a smaller section. The choice depends on the location and extent of compression.
During a discectomy, the surgeon removes damaged disc material pressing on a nerve. This may ease leg or arm pain, although numbness can take longer to improve.
Spinal fusion joins two or more vertebrae with bone graft material and stabilization hardware. It may help when movement causes pain or when the spine is unstable. In more complex cases, a corpectomy removes part or all of a vertebral body and replaces the lost support.
Recovery varies widely. Some patients walk on the day of surgery, while others need several weeks of structured rehabilitation. Pain, infection, blood clots, nerve injury, and failed fusion are recognized risks. A careful surgeon reviews imaging, physical findings, bone health, and daily goals before recommending an operation.
No technique is perfect. A wider surgical exposure may improve access, but it can also increase muscle injury and recovery time. That trade-off deserves honest discussion. Patients should ask what problem the operation targets, what alternatives exist, and how success will be measured. Clear expectations matter as much as the surgical plan.
Minimally Invasive Spine Surgery Techniques
Minimally invasive spine surgery uses smaller incisions and specialized instruments to reduce muscle disruption. Surgeons may use tubular retractors, an endoscope, or a microscope to reach the spine through a narrow pathway. The goal is focused treatment, not simply a smaller scar. Patients may experience less blood loss, reduced postoperative pain, and earlier movement. Results still depend on the diagnosis, overall health, and surgical experience.
Common techniques include endoscopic discectomy for selected herniated discs and minimally invasive decompression for nerve pressure. Percutaneous screws can stabilize certain spinal fractures or unstable segments. Real-time imaging helps guide these instruments around delicate nerves. A surgeon should explain the images, expected benefits, possible complications, and non-surgical options in clear language. I find that detailed questions often reveal whether the proposed technique truly fits the patient.
Smaller does not always mean safer. Some complex deformities, infections, or severe instability may require traditional exposure. Even careful planning is not perfect. Symptoms can persist, and nerve recovery may take months. Recovery often includes short walks, wound monitoring, and restrictions on lifting. Patients should report fever, increasing weakness, drainage, or loss of bladder control promptly. A qualified spine specialist can compare minimally invasive and open approaches using the patient’s examination and imaging, rather than relying on a fashionable procedure.
Recovery, Risks, and Expected Outcomes
Spine surgery is not one operation. Common techniques include decompression, microdiscectomy, spinal fusion, and artificial disc replacement. Recovery depends more on diagnosis than on the incision size. In the SPORT trial, which followed 1,244 patients with lumbar disc herniation, surgery produced sustained improvements in pain and function over eight years. However, improvement was not identical for every patient. NASS clinical guidelines stress matching surgery to symptoms, imaging, and neurological findings.
Recovery may take several weeks after decompression, while fusion often requires several months for solid bone healing. Early walking is usually encouraged, but lifting, bending, and driving may remain restricted.
Risks include infection, blood clots, nerve injury, recurrent disc herniation, nonunion, and persistent pain. The American College of Surgeons’ NSQIP data show that complications after major surgery remain measurable, even when rates are low. A technically successful operation cannot repair every pain pathway. That limitation deserves honesty.
Tips: Ask what improvement is realistic, not merely possible. Request the surgeon’s complication and revision rates for your exact procedure. Bring a medication list and report new leg weakness promptly. The evidence is not tidy. Some studies favor surgery; others show similar long-term results with structured nonoperative care. A second opinion can expose overlooked options, especially when pain is severe but neurological damage is absent. Expect progress in small steps: a shorter walk, better sleep, and safer movement may appear before pain fully settles.
Related Posts
-
China Top 10 Spine Surgery Device Manufacturers
-
How to Prepare for Spinal Fusion Surgery?
-
How to Effectively Treat Bone Fractures for Faster Recovery?
-
How to Improve Musculoskeletal Health at Work?
-
China Top Innovations in Bone Regeneration Medicine for Better Health?
-
What Is Orthopedic Implant Technology?